Morning Sickness: Causes, Severity and What Actually Helps

If you are reading this while lying on the bathroom floor, or eating plain crackers at 2am, or cancelling plans because the smell of cooking made you retch, this article is for you. Morning sickness is one of the most common experiences in early pregnancy and one of the most poorly managed. It is rarely just in the morning. It can last all day, every day, for weeks. It can make it very hard to eat, to work, to function. You deserve practical information about what is actually causing it and what the evidence says genuinely helps.
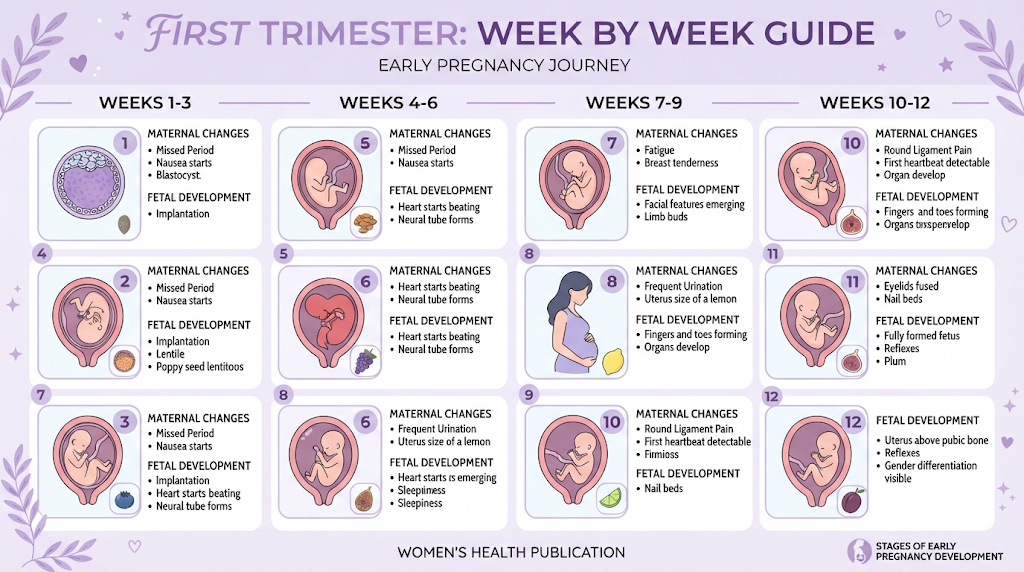
Pregnancy nausea and vomiting, commonly called morning sickness, affects around 70 to 80 percent of pregnant women and is most commonly caused by rising levels of human chorionic gonadotropin (hCG) and oestrogen in early pregnancy. It typically begins around weeks 5 to 6, peaks between weeks 8 and 10, and resolves for most women by weeks 12 to 16. Evidence-supported approaches include eating small frequent meals, ginger, vitamin B6, acupressure wristbands, and, when needed, antiemetic medication prescribed by a healthcare provider. Hyperemesis gravidarum is a severe form requiring medical treatment and should never be managed at home alone.
What Causes Morning Sickness
The exact cause of pregnancy nausea is not fully understood, but the most well-supported explanation links it to rapidly rising hCG levels. hCG is produced by the developing placenta from the moment of implantation and rises steeply through the first trimester, peaking around weeks 8 to 10. The timing of nausea mirrors this curve closely, which is why it typically eases as hCG begins to plateau and the placenta matures.
Rising oestrogen is also thought to contribute, as it can stimulate the chemoreceptor trigger zone in the brain that initiates nausea and vomiting. Progesterone slows gastric emptying by relaxing smooth muscle in the digestive tract, meaning food stays in the stomach longer and nausea is prolonged.
Women carrying multiple pregnancies, who have higher hCG levels, tend to experience more severe nausea. A history of motion sickness or migraines, a previous history of severe morning sickness, and a family history of hyperemesis gravidarum are all associated with a higher likelihood of significant nausea in pregnancy.
The Spectrum: Mild to Severe
Pregnancy nausea exists on a wide spectrum. At the milder end, some women experience background queasiness that does not significantly affect their eating or daily functioning. At the more moderate level, nausea is persistent and disruptive: it affects the ability to eat normally, makes some foods intolerable, interferes with concentration and work, and causes genuine misery. Vomiting may occur once or several times daily.
At the severe end sits hyperemesis gravidarum (HG), a distinct clinical condition affecting around 1 to 3 percent of pregnancies. HG involves persistent, severe vomiting that prevents adequate nutrition and hydration, causes weight loss of more than 5 percent of pre-pregnancy body weight, and leads to dehydration and electrolyte imbalance. HG is not morning sickness that is “just a bit worse.” It is a serious condition that requires medical management.
What Actually Helps: Evidence-Based Approaches
Eating small, frequent meals
An empty stomach worsens nausea. Keeping something light in the stomach throughout the day, before hunger becomes acute, is one of the most consistently recommended approaches. Many women find plain, bland carbohydrates most tolerable: crackers, plain rice, toast, boiled potato. Eating before getting out of bed in the morning (keeping crackers by the bedside) can reduce the intensity of early morning nausea for some women.
Ginger
Ginger is the most widely studied natural remedy for pregnancy nausea, and the evidence supports its use. Studies on ginger supplements, ginger tea, and ginger biscuits all show meaningful reduction in nausea severity compared to placebo, with a good safety profile. Ginger capsules standardised to 125 to 250 milligrams taken up to four times daily are the form used in most research. Ginger ale made with real ginger, ginger tea, or crystallised ginger can also help.
Vitamin B6 (pyridoxine)
Vitamin B6 is a first-line recommended treatment in many clinical guidelines for pregnancy nausea. It is available over the counter in many countries and has a well-established safety record in pregnancy. A typical dose used in research is 10 to 25 milligrams taken three times a day. In some countries, a combination tablet of vitamin B6 and doxylamine (an antihistamine) is available and is among the most studied antiemetic treatments for pregnancy nausea. Discuss dosing with a pharmacist or healthcare provider.
Acupressure
Acupressure wristbands, which apply pressure to the P6 (Neiguan) point on the inner wrist, have evidence from several trials supporting a modest reduction in nausea. They are safe, inexpensive, and available without prescription. While the effect size is not large, they are a reasonable option to try alongside dietary measures, particularly for women who prefer to start with non-pharmacological approaches.
Hydration
Nausea makes it harder to drink, but dehydration worsens nausea, creating a difficult cycle. Sipping cold, clear fluids frequently rather than drinking large amounts at once tends to be better tolerated. Sparkling water, diluted squash, or ice chips can all help maintain fluid intake when larger volumes feel impossible. Electrolyte drinks or oral rehydration solutions can be helpful if vomiting has been frequent.
Avoiding triggers
Strong smells are a common trigger. Cooking odours, perfume, cigarette smoke, and certain foods can provoke immediate nausea in many pregnant women. Cold foods often have less odour than hot ones and may be better tolerated. Good ventilation during cooking, asking a partner or household member to cook when possible, and eating foods at room temperature can reduce exposure.
Medication Options
For women whose nausea is significantly affecting quality of life, eating, or the ability to function, medication is appropriate and available. Effective, pregnancy-safe antiemetic medications exist and are used in healthcare systems worldwide. These include antihistamines such as promethazine and cyclizine, metoclopramide, ondansetron, and the combination of vitamin B6 and doxylamine mentioned above.
None of these should be taken without discussion with a healthcare provider, who can assess which option is most appropriate at the current stage of pregnancy and in the context of any other health factors. The key message is this: medication for pregnancy nausea is not a last resort for people who cannot cope. It is appropriate, evidence-based treatment for a condition that causes real harm to quality of life. There is no benefit to suffering through severe nausea when treatment is available.
Hyperemesis Gravidarum: Recognising and Treating It
Hyperemesis gravidarum requires medical treatment and cannot be effectively managed at home alone. It is not a reflection of weakness or poor coping. It is a physiological condition that, without treatment, causes malnutrition, dehydration, and serious pregnancy complications.
Signs that nausea and vomiting have crossed into hyperemesis gravidarum territory include: inability to keep any food or fluid down for 24 hours or more, dark urine or no urination (signs of dehydration), dizziness when standing, vomiting blood or bile, significant unintentional weight loss, and extreme weakness.
Treatment for HG typically involves intravenous fluids to correct dehydration and electrolyte imbalance, intravenous or intramuscular antiemetics, nutritional support, and in severe cases, hospitalisation. Thiamine (vitamin B1) supplementation is important in HG as severe vomiting can deplete thiamine levels, and deficiency can cause serious neurological complications. Women with HG may require ongoing medication and support throughout pregnancy, not just in the first trimester.
When to Seek Help
Seek assessment from a healthcare provider if: you are unable to keep fluids down for more than 24 hours, you are losing weight, your urine is very dark or you are urinating much less than usual, you feel dizzy or faint when standing, or your nausea and vomiting are significantly affecting your ability to function. Do not wait to see if it improves. Assessment is appropriate and early treatment prevents deterioration.
FAQ
Does morning sickness mean the pregnancy is healthy?
Nausea in early pregnancy has been associated in some studies with a lower risk of miscarriage, likely because it reflects robust hCG production. However, the absence of nausea does not indicate an unhealthy pregnancy. Many women with entirely healthy pregnancies experience little or no nausea. Nausea is not a health barometer, and the absence of it is not a warning sign on its own.
Is it safe to take antiemetics in pregnancy?
Several antiemetic medications have been studied in pregnancy and are considered appropriate to use under medical supervision. These include antihistamines such as cyclizine and promethazine, metoclopramide, and ondansetron, among others. No medication should be taken in pregnancy without guidance from a healthcare provider, who can advise on the most appropriate option for the stage of pregnancy and individual circumstances. Untreated severe nausea and vomiting also carries risks to both mother and pregnancy.
How long does morning sickness last?
For most women, nausea peaks between weeks 8 and 10 and eases significantly by weeks 12 to 16. A smaller proportion of women continue to experience nausea into the second trimester, and a minority have symptoms that persist throughout pregnancy. Hyperemesis gravidarum can continue beyond the first trimester and in some cases requires management for the duration of the pregnancy. If symptoms have not improved by week 16, discuss this with a healthcare provider.
Can morning sickness harm the baby?
Mild to moderate morning sickness does not typically harm the baby, even if it significantly affects the mother. Difficulty eating varied foods in the first trimester is common and the foetus generally draws on maternal reserves. However, severe and prolonged nausea and vomiting, particularly hyperemesis gravidarum, can cause complications including low birth weight and preterm birth if not treated. This is another reason why severe symptoms warrant medical management rather than endurance.
You Should Not Have to Just Suffer Through It. Mayno Is Here to Help You Find What Works.
Morning sickness is real, it is hard, and it is treatable. Whether you need information, reassurance, or a clear guide to what options are available to you, Mayno is here to support you through every part of the early pregnancy journey.
Visit mayno.health for pregnancy health guidance written with honesty and care.
This article is for informational purposes only and does not constitute medical advice. If you are pregnant and experiencing significant nausea or vomiting, please consult a qualified healthcare professional. Mayno Health does not replace clinical care.
Disclaimer: This article is for informational purposes only and does not constitute medical advice. Always consult a qualified healthcare professional.